
https://www.gosh.nhs.uk/conditions-and-treatments/clinical-outcomes/selective-dorsal-rhizotomy-clinical-outcomes/
Selective Dorsal Rhizotomy clinical outcomes
If you would like this information in another language or format, please contact the Patient Advice and Liaison Service (PALS).
Clinical outcomes are measurable changes in health, function or quality of life that result from our care. Constant review of our clinical outcomes establishes standards against which to continuously improve all aspects of our practice.
About the Selective Dorsal Rhizotomy service
GOSH established its Selective Dorsal Rhizotomy (SDR) service in 2013 and is one of five centres providing the service in England. SDR is an operation that reduces spasticity (muscle stiffness) in children with cerebral palsy who are identified as suitable candidates in a multidisciplinary clinic.
Spasticity can impair movement and coordination, cause pain, and over time can cause shortening of muscles and tendons, joint contractures and bone deformities. Nerves running from the leg muscles to the spinal cord play a major role in spasticity. The SDR operation, in which some of these nerves are divided, can be very effective at reducing spasticity and improving quality of life.
SDR is the only procedure to permanently remove spasticity in the legs of children with cerebral palsy. However, it is not a suitable treatment for every patient, so full assessment and preparation in a multidisciplinary clinic are an essential part of the care we provide.
The Gross Motor Function Classification System (GMFCS) is an internationally recognised system for grading gross motor function in children with cerebral palsy. The levels are I to V, where those at level I have the least functional limitations, and those at level V the greatest functional limitations.
The SDR service at GOSH has been active since early 2013 and a total of just under 350 children have undergone the procedure to date. The following outcomes relate to the 97 children in GMFCS levels II and III who underwent SDR surgery between 2020 and 2023 at GOSH.
The primary aim of SDR is to improve quality of life of children with spastic cerebral palsy. However, the specific outcome goals vary depending on the GMFCS level. For children in levels II and III, the primary aim is to improve function, mobility and comfort. For level IV children, the aim is to improve comfort and care giving. SDR in level IV children is not funded by the NHS and numbers of children referred are therefore small. We have recently published our results for these children in the British Journal of Neurosurgery.
Clinical outcome measures
Measures of the treatment effectiveness of SDR include surgical and specialist therapy outcomes.
1. Modified Ashworth Scale (MAS)
The MAS measures resistance during muscle stretching and is used to assess the effectiveness of treatment to reduce spasticity. A study of 30 children undergoing SDR between 2014 and 2018 recorded average MAS scores for leg muscle groups. We test the lower limbs (adductors, hip flexors, knee flexors and plantar flexion), and they are scored from 0 (normal tone) to 4 (rigid tone). Average scores for all lower limb muscle groups before surgery were between 2 and 4. At two years post-surgery the average score was 0 for 97% of children (n = 29/30) indicating a reduction in spasticity. One child had minimal residual muscle tone in a single muscle group. All 30 children had improvements in MAS scores of one point or more for all muscle groups.
The MAS assessment is completed up to one month prior to surgery, and at six months, one year and two years post-surgery. The average score at each time point is compared to see the early effect of surgery on the child’s spasticity and the effect over time. The data shows that MAS scores improved after surgery, and the improvement was sustained over time, confirming that SDR is very effective in permanently reducing spasticity.
*Note: data for MAS scores will be updated in December 2026.
2. Gross Motor Function Measure (GMFM)
Gross motor skills are involved in the movement, balance and coordination of the body. The GMFM is an internationally recognised standardised assessment tool used by specialist paediatric physiotherapists to evaluate change in gross motor function in children with cerebral palsy. The measure has a scoring system across the five categories: lying and rolling; sitting; crawling and kneeling; standing; walking, running and jumping. To measure progress after surgical and therapy interventions, we use the GMFM-66, in which a child’s gross motor function is observed and tested against 66 standardised items.
The GMFM-66 assessment is completed pre-surgery, and after surgery at six months, one year and two years post-surgery. The average scores at each time point are compared to see the early effect of surgery on the child’s gross motor skills and the effect over time.
2.1.1 GMFCS Level II and Level III
We report here data on GMFM-66 for 97 children at GMFCS levels II and III, who had SDR surgery at GOSH between February 2020 and October 2023.
The average increase in GMFM-66 for children in GMFCS level II is 6.37 (from 75.80 pre-surgery to 82.17 two years post-surgery). For children with a GMFCS level III the average increase is 5.66 (from 57.24 pre-surgery to 62.90 two years post-surgery). This difference is statistically significant and clinically relevant.
Figure 2.1.1 Average GMFM pre- and post-surgery by GMFCS level
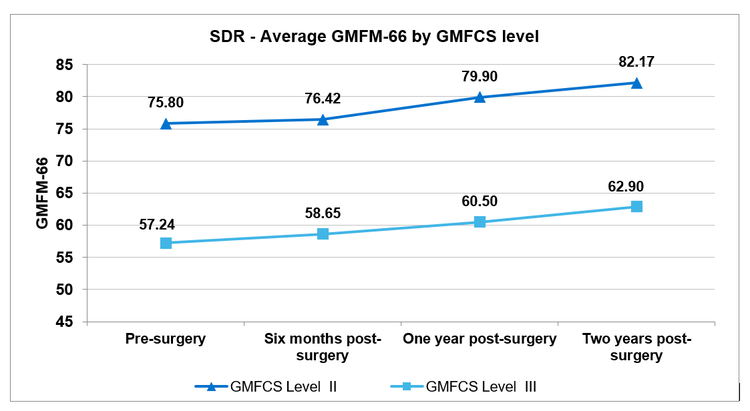
The change in GMFM-66 score for individual children from before surgery to two years post-surgery ranges from -0.76 to 23.24. A small number of children had a decrease in GMFM-66 score. While children’s GMFM-66 score generally increased at two years post-surgery, some have moderate improvement or maintained function.
2.1.2. Cerebral Palsy Quality of Life (CP QOL-Child)
The CP-QoL is a questionnaire about quality of life for children and young people with cerebral palsy. The questions cover general and social wellbeing, function, physical health, self-esteem, pain, impact of disability, schooling, and family health. We use the primary caregiver questionnaire for all our patients.
The CP-QoL primary caregiver questionnaire is completed pre-surgery, and after surgery at six months, one year and two years post-surgery. An average score is calculated for the seven areas using the answers to individual questions within that area. Scores are based on responses at a specific ‘snapshot’ in time. Below we show the average scores pre-surgery and at two years post-surgery, by GMFCS level.
We report here data on CP-QoL for 97 children with GMFCS levels II and III who had SDR surgery at GOSH between February 2020 and October 2023.
Table 2.1.2 Average CP-QoL scores at pre- and two years post-surgery by GMFCS, Level II and III
| GMFCS Level II (n = 37) and Level III (n = 60) | Pre-surgery | 2 years post-surgery | |
|---|---|---|---|
| Access to services | GMFCS Level II | 53.76 | 53.56 |
| GMFCS Level III | 55.47 | 54.55 | |
| Emotional wellbeing and self-esteem | GMFCS Level II | 79.24 | 79.51 |
| GMFCS Level III | 80.58 | 77.55 | |
| Feelings about functioning | GMFCS Level II | 73.24 | 76.07 |
| GMFCS Level III | 74.11 | 73.11 | |
| Family health | GMFCS Level II | 72.78 | 70.90 |
| GMFCS Level III | 67.65 | 62.63 | |
| Pain and impact of disability* | GMFCS Level II | 36.30 | 34.44 |
| GMFCS Level III | 37.60 | 36.31 | |
| Participation and physical health | GMFCS Level II | 56.81 | 66.54 |
| GMFCS Level III | 60.82 | 61.44 | |
| Social wellbeing and acceptance | GMFCS Level II | 80.02 | 80.36 |
| GMFCS Level III | 80.65 | 77.42 |
* For ‘pain and impact of disability’ section a lower average score indicates a reduction in pain and impact of disability.
For questions on feelings about functioning, and participation and physical health, the average CP-QoL caregiver scores generally improve between pre-surgery and 2 years post-surgery.
For questions on the pain and impact of disability the average scores decrease (indicates a reduction in pain and impact of disability) between pre-surgery and 2 years post-surgery.
For questions on social wellbeing and acceptance, the average scores increase for children with a GMFCS level II but decrease for children with a GMFCS level III. This has also been described in other studies. Children in the GMFCS III group become more aware of their disabilities as they grow, and this may impact their perceptions of social wellbeing and acceptance.
For questions on emotional wellbeing and acceptance, the average scores increase for children with a GMFCS level II and decreases for children with a GMFCS level III.
For questions on access to services the average scores decrease for children with a GMFCS level II or III. This is one issue we hope to explore and try to address over the coming year.
3. Complications of SDR surgery
Every surgical procedure carries risk. It is essential to collect data on complications or ‘adverse events’ to have an accurate understanding of both risk and surgical performance. This is turn informs the consent process for future patients and their families considering surgery. We collect data on the following complications associated with SDR surgery: surgical site infection (superficial incisional; deep incisional; organ/space); bleeding that requires return to theatre; cerebrospinal fluid (CSF) leak; and permanent incontinence due to surgery.
Table 3.1 Complications of SDR surgery, 2020/21 to 2025/26
| Year | Total number of operations | Infection |
Bleeding that requires return to theatre |
CSF leak | Permanent incontinence due to surgery |
|---|---|---|---|---|---|
| 2020/21 | 21 | 0 | 0 | 0 | 0 |
| 2021/22 | 33 | 0 | 0 | 0 | 0 |
| 2022/23 | 29 | 0 | 0 | 0 | 0 |
| 2023/24 | 24 | 0 | 0 | 0 | 0 |
| 2024/25 | 33 | 0 | 0 | 0 | 0 |
| 2025/26 | 26 | 0 | 0 | 0 | 0 |
| Total | 166 | 0 | 0 | 0 | 0 |
References
- Summers, J et al., Selective dorsal rhizotomy in ambulant children with cerebral palsy: an observational cohort study, The Lancet Child & Adolescent Health, 2019, 3:455-462.
- McLaughlin, J. et al., Selective dorsal rhizotomy: meta-analysis of three randomized controlled trials, Developmental Medicine & Child Neurology, 2002, 44: 17–25.
- Engsberg, J.R. et al., Effect of selective dorsal rhizotomy in the treatment of children with cerebral palsy, Journal of Neurosurgery, 2006, 105(1 Supplement): 8–15.
- Nordmark, E. et al., Long-term outcomes five years after selective dorsal rhizotomy, BMC Pediatrics, 2008, 8:54.
- van Schie, P. E. M. et al., Short- and long-term effects of selective dorsal rhizotomy on gross motor function in ambulatory children with spastic diplegia, Journal of Neurosurgery Pediatrics, 2011, 7:557-562.
- Elnaggar, A. M. et al., Selective dorsal rhizotomy – the treatment of choice for cerebral palsy spasticity in non-ambulant GMFCS IV children?, British Journal of Neurosurgery, 2026, 1–10. doi: 10.1080/02688697.2026.2661339.